

Ostarine (MK-2866): Results, Before and After Pictures, Dosages
 Disclaimer: SARMs are not FDA-approved and may cause adverse effects in animal models or human subjects. Dr. Touliatos is available for consultation should readers have any questions or concerns.
Highlights
- Our observations of user before-and-after transformations suggest that Ostarine may benefit researchers exploring muscular strength and hypertrophy.
- Some athletes take Ostarine for performance-enhancement purposes, helping them achieve their sporting goals. However, major sporting organizations prohibit selective androgen receptor modulator (SARM) use, such as the World Anti-Doping Agency (WADA), the United States Anti-Doping Agency (USADA), and the International Olympic Committee (IOC).
- We have discovered that Ostarine appears to possess a lower toxicity profile for promoting anabolism in subjects compared to other SARMs.
- We recommend Sports Technology Labs and SwissChems for researchers seeking high-purity, laboratory-tested Ostarine. These companies’ third-party certificates of analysis (COAs) ensure product quality and authenticity.
- Our doctors’ clinical observations indicate that Ostarine may cause toxicity to the liver and heart. Therefore, it is not suitable for individuals with elevated liver enzymes or hypertension, who may be particularly vulnerable to harm.
Contents
- 1 Highlights
- 2 What is Ostarine?
- 3 Best SARM Companies in 2026
- 4 Ostarine Before and After Results (45 Days)
- 5 Ostarine Before and After Pictures (5 Weeks)
- 6 Ostarine Before and After Transformation (8 Weeks)
- 7 Ostarine Dosages Utilized in Research
- 8 What Are the Potential Benefits of Ostarine? Key Research Findings
- 9 What Are the Potential Side Effects of Ostarine? Research Findings
- 10 Ostarine Cycles
- 11 Ostarine and GW501516 Cycle
- 12 How Can Researchers Administer Ostarine?
- 13 Top 5 Ostarine Sources: Tailored Recommendations for Researchers
- 14 Frequently Asked Questions
- 15 Ostarine Data and Information
- 16 Safety Guidelines
- 17 Ostarine vs. Anavar: What Are the Key Differences?
- 18 Summary: What Are the Pros and Cons of Ostarine?
- 19 Resources
- 20 Relevant Research
What is Ostarine?
Ostarine, a second-generation SARM, is also known as:
- Enobosarm
- MK-2866
James T. Dalton, Ph.D., is the pioneer who created Ostarine with his research team in the early 2000s. He states that the objective of Ostarine is to mimic the anabolic effects of steroids without the harsh side effects.
Ostarine has attracted interest from researchers seeking innovative treatments for patients suffering from:
- Cachexia
- Osteoporosis
- Anemia
What Are the Origins of Ostarine?
GTx, Inc., a United States (US) biotechnology firm, first described and developed MK-2866 in 2001. Since then, phase 1, 2, and 3 clinical trials have evaluated the SARM.
In phase 3 trials, GTx announced that Ostarine failed to treat cachexia in patients with breast cancer.
The treatment failed because it produced insignificant strength improvements, even though patients gained muscle.
This failure led GTx to stop pursuing Ostarine for the treatment of cachexia. However, the biotechnology company remains committed to modifying MK-2866 to improve its future success.
Is Ostarine FDA-Approved?
The Food and Drug Administration (FDA) has not approved Ostarine for human use. Additionally, sporting organizations have prohibited Ostarine’s use for athletic purposes, including:
- The World Anti-Doping Agency (WADA)
- The US Anti-Doping Agency (USADA)
- The International Olympic Committee (IOC)
The law also prohibits people from administering Ostarine for cosmetic purposes, with only scientific research permitted.
Such legislation has led SARM manufacturers to modify their marketing strategy, labeling products as research chemicals instead of dietary supplements, effectively capitalizing on this opportunity.
Travis Tygart, chief executive officer (CEO) of USADA, has stated that he is examining “legislative options” to remove Ostarine and other SARMs from the market.
Best SARM Companies in 2026
Disclosure: Inside Bodybuilding does not accept third-party advertising. Our revenue is generated through doctor consultations and carefully curated SARM recommendations for research applications.
Swiss Chems

Swiss Chems is our recommended source for SARM capsules, guaranteeing a minimum purity of 99% across all its products.
Swiss Chems offers worldwide shipping, allowing non-US researchers to access high-quality SARMs.
US orders are delivered within 3–7 business days, while international orders typically arrive in 2–3 weeks.
Sports Technology Labs

Sports Technology Labs is a highly cost-effective liquid SARM source for US researchers, offering purity levels exceeding 98%, as confirmed by its certificates of analysis.
Sports Technology Labs also has a no-credit-card-fee policy, whereas other sources can charge up to 10%.
Sports Technology Labs does not currently provide shipping outside the US.
Note: Sports Technology Labs’ products are regularly tested by MZ Biolabs, an independent laboratory with a US Drug Enforcement Administration Schedule III license.
Ostarine Before and After Results (45 Days)
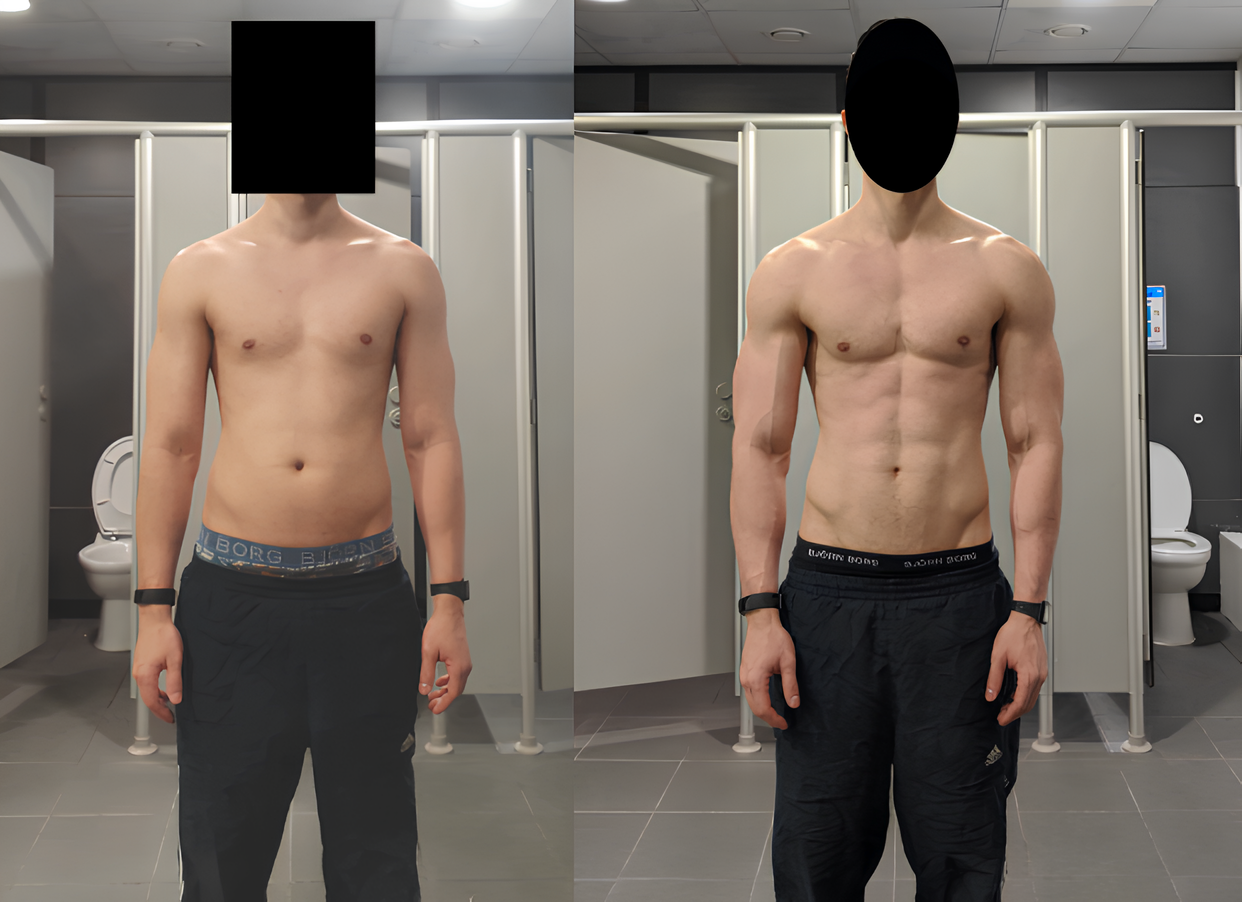
The Reddit user achieved these results by taking 20 milligrams per day (mg/day) of Ostarine for 45 days, combined with:
- Conventional weight training methods
- A balanced diet
The user lost 3 kg (7 lb), yet he appears increasingly muscular. Enhanced muscle definition explains the change rather than increased hypertrophy.
We find this user’s results to be above average. Coincidentally, they were training more regularly on Ostarine, which contributed to additional muscle development and fat loss.
Ostarine Before and After Pictures (5 Weeks)
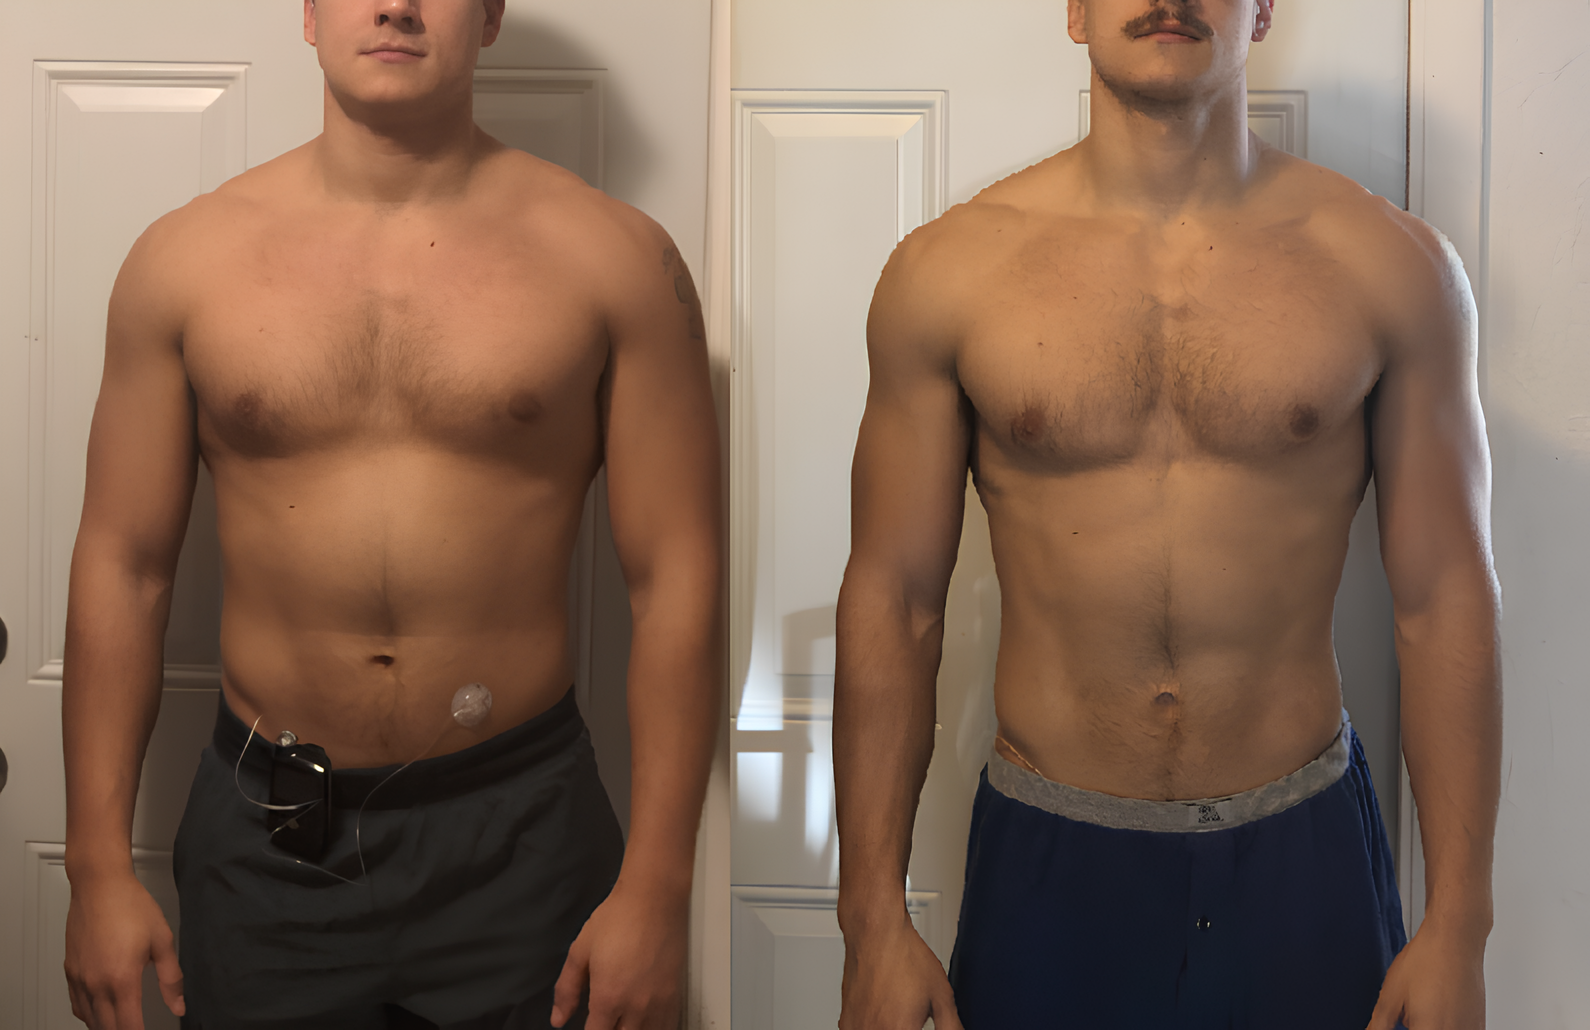
This Reddit user lost 13 lb after cycling Ostarine for 6 weeks. They administered:
- 12.5 mg/day during week 1
- 25 mg/day for the remaining 5 weeks
The male user did not report any obvious side effects. However, we advise users to have a physician check their health to rule out potential organ deterioration or hormone fluctuations.
They experienced notable fat loss, accompanied by increased muscle fullness and vascularity. Eating in a calorie deficit contributed to some of the fat loss during this transformation.
The user believes Ostarine did not aid him in gaining muscle mass but likely helped retain it during his cycle. Their strength levels remained stable throughout the 6 weeks of use.
Ostarine Before and After Transformation (8 Weeks)
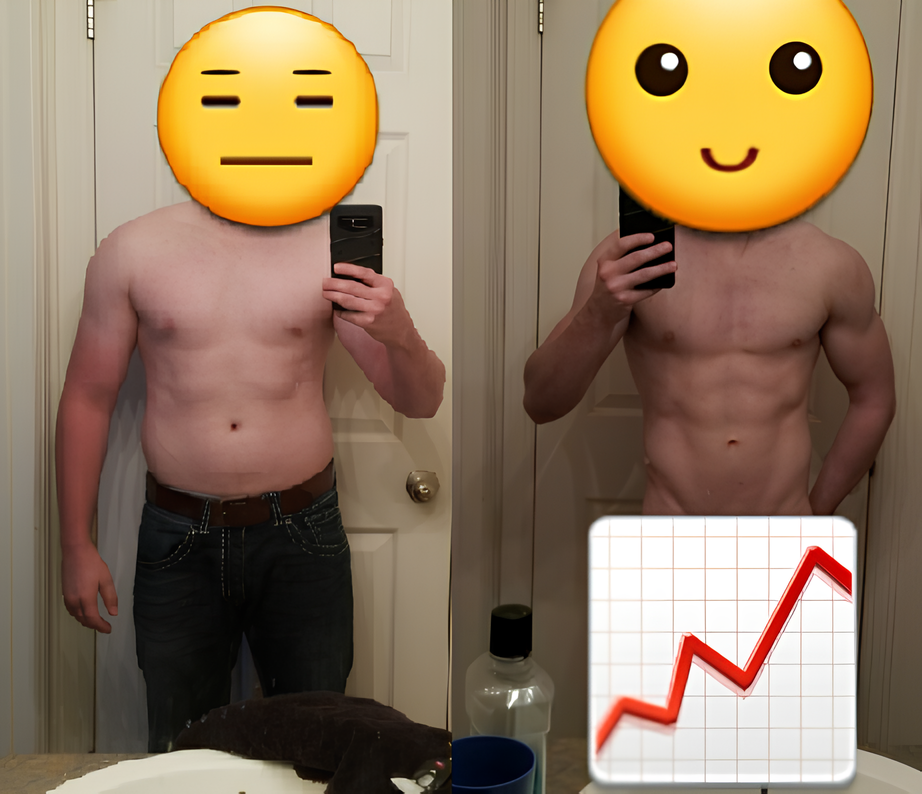
This Reddit user lost 23 lb after administering 20 mg/day for 8 weeks.
The user maintained a calorie deficit during their Ostarine cycle, contributing to substantial fat loss. The individual did not gain any muscle mass, despite vast improvements in muscle definition.
Their strength levels did not increase. However, they credit Ostarine for preserving muscle hypertrophy and strength while consuming fewer calories—specifically, 1,800 per day.
In terms of side effects, the user reported:
- High liver enzymes, with an alanine aminotransferase (ALT) score of 57 international units per liter (IU/L).
- Low testosterone levels post-cycle, measuring 270 nanograms per deciliter (ng/dL).
After transitioning into a hypogonadal state, they were eligible for prescribed testosterone replacement therapy. The user reported physiological and psychological decline post-cycle, including:
- Feeling jaded
- Experiencing diminished well-being
- Low energy
The individual did not report feeling ‘a high’ during the Ostarine cycle, yet they experienced this decline.
Our patients’ results from Ostarine are comparable to a mild Anavar (oxandrolone) or Winstrol (stanozolol) protocol, with muscle hypertrophy and fat loss occurring synergistically (1). Ostarine, Anavar, and Winstrol also share similar side effects, negatively affecting the liver, heart, and HPTA.
Ostarine Dosages Utilized in Research

Regulators have not established dosage guidelines for Ostarine due to a lack of FDA approval. However, clinical studies have successfully administered daily doses of:
- 3 mg
- 9 mg
- 18 mg
However, higher Ostarine dosages can exacerbate side effects, including:
- Cholesterol levels
- Liver values
- Testosterone suppression
What Are the Potential Benefits of Ostarine? Key Research Findings
- Muscle size and strength
- No virilization in women
- Fat loss
Muscle Size and Strength
Ostarine works similarly to an anabolic steroid by activating the androgen receptor, increasing bone and muscle strength. Ostarine also enhances the activation of satellite cells, leading to:
- The fusion of myofibers
- Increased number of myonuclei within the muscles
Because Ostarine targets specific tissues, it builds lean muscle without the androgenic side effects of anabolic steroids. This mechanism of tissue selectivity prevents benign prostatic hyperplasia.
In one study involving elderly men and women, participants increased their lean body mass by 3% after consuming 3 mg/day of Ostarine for 12 weeks (2). This is the equivalent of an 80 kg (176 lb) man gaining 2.4 kg (5.3 lb) of muscle.
The elderly subjects also experienced significant increases in muscular strength, adding 22 lb, on average, to their bench presses by the 12th week.
No Virilization in Women
Women are particularly vulnerable to virilization effects when taking steroidal compounds. However, elderly women in the above-cited study experienced no masculinization effects with Ostarine.
Fat Loss
Ostarine is an efficacious SARM for stimulating lipolysis by increasing insulin sensitivity, which in turn promotes the loss of subcutaneous and visceral fat.
The reduction of visceral fat (VF) is a unique attribute of Ostarine, in contrast to various anabolic steroids that increase VF. This characteristic elucidates why some steroid users develop a distended waistline, an indication of elevated VF levels.
Thus, Ostarine promotes fat loss throughout the body, particularly in the midsection, reducing overall waist circumference.
Ostarine also possesses positive metabolic effects, increasing calorie expenditure and satiety. Thus, it has direct and indirect lipolytic effects.
In the elderly study, users experienced a 0.6 kg (1.3 lb) reduction in fat mass. We have observed additional fat loss in non-elderly users on Ostarine when combined with:
- Standard weightlifting
- Cardiovascular exercise
Thus, being sedentary is likely to inhibit fat loss on Ostarine.
What Are the Potential Side Effects of Ostarine? Research Findings
- Testosterone suppression: The extent of this adverse effect appears to be dose-dependent.
- Liver toxicity: Ostarine and other SARMs may replicate the hepatotoxic effects of various anabolic steroids.
- Cholesterol issues: Deteriorated lipid profiles have been documented in research, increasing cardiovascular risks for users.
- Gynecomastia and water retention: Some users have reported estrogen-related side effects, indicating that Ostarine is not entirely tissue selective.
- Hair loss: There have been anecdotal reports of Ostarine causing androgenic side effects, including hair thinning or loss on the scalp.
Mike Israetel, Ph.D., M.S., states that SARMs in general have “comparable side effects” to anabolic-androgenic steroids. However, Dr. Israetel adds that certain SARMs, such as Ostarine, may be “safe” and “effective.”
Ostarine does not cause hypertrophy of the prostate; however, it does reproduce several other anabolic steroid side effects. Therefore, researchers cannot yet regard Ostarine as safe for humans.
Testosterone Suppression
The men in the cited elderly study who took 3 mg/day of Ostarine for 12 weeks experienced minimal fluctuations in their serum testosterone levels. Some of our patients who have taken higher doses of Ostarine, including 25 mg/day, have reported the following:
- Standard libido
- Nocturnal erections
- Increased testicular volume
However, in other users, Ostarine lowers testosterone levels post-cycle. This suppression suggests that excessive androgen-receptor stimulation negatively affects the HPTA.
Thus, Ostarine has no significant effect on endogenous testosterone levels when taken in conservative dosages. However, Ostarine exhibits a suppressive effect at elevated doses, which may not invariably result in perceivable side effects.
Researchers widely regard Ostarine as less potent than anabolic steroids; therefore, a complete shutdown of the HPTA is unlikely.
Nicholas Downey, M.D., states that in rodents, luteinizing hormone and follicle-stimulating hormone levels remain largely “unaffected” by Ostarine. However, Dr. Downey adds that prolactin “may be an issue” in sensitive subjects utilizing Ostarine because it is a weak antagonist of the progesterone receptor.
Liver Toxicity
In the elderly study, aspartate aminotransferase (AST) and ALT levels increased above baseline in 20% of participants. Such elevations indicate Ostarine’s hepatotoxic potential.
Ostarine’s oral route contributes to its potential liver toxicity, as it must bypass the liver before becoming fully active.
Our patients’ liver function tests indicate that Ostarine can mimic hepatotoxicity to the same extent as potent oral anabolic steroids in certain individuals. Our head physician, Thomas O’Connor, M.D., states that he did not observe significant differences in liver markers when a patient switched from Dianabol (methandrostenolone) and Anadrol (oxymetholone) to Ostarine.
Other SARMs, such as RAD-140 (testolone) and LGD-4033 (ligandrol), have also caused hepatocellular-cholestatic liver injury in some of our patients (3).
Cholesterol Issues
A clinical study found that 3 mg/day of Ostarine for 12 weeks led to a 27% reduction in high-density lipoprotein (HDL) cholesterol. This study’s modest dosage and the consequent alterations in cholesterol raise concerns about Ostarine’s potential cardiotoxicity.
Thus, Ostarine can increase the risk of myocardial infarction in the short or long term, even in modest doses.
The oral nature of Ostarine and other SARMs could be related to their adverse effects on:
- HDL cholesterol
- Low-density lipoprotein (LDL) cholesterol
SARMs may negatively affect cardiovascular health by stimulating hepatic lipase upon entry, an enzyme that can lower HDL and promote arterial plaque.
Gynecomastia and Water Retention
Several SARMs elevate estrogen indirectly via binding to the androgen receptor. This leaves additional testosterone free and available to convert to estrogen.
Consequently, some of our patients have become bloated or developed gynecomastia when using SARMs, despite a lack of aromatization (4). However, their muscles may look drier with Ostarine due to decreased extracellular fluid.
Furthermore, improved insulin sensitivity from Ostarine also indicates its minimal effect on estrogen, thereby reducing the likelihood of:
- Gynecomastia
- Water retention
- Increased abdominal fat
Hair Loss
A subset of our patients has experienced hair loss or recession during Ostarine use, despite the absence of 5-alpha-reductase enzyme activity. The main culprit behind androgenetic alopecia is elevated dihydrotestosterone (DHT) levels.
Increases in DHT occur indirectly as Ostarine competes with users’ natural testosterone when binding to the androgen receptor. In this instance, Ostarine is the more potent substance, causing surplus free testosterone to convert to DHT.
Although Ostarine causes hair loss less often than anabolic steroids, androgenetic alopecia remains possible.
Ostarine Cycles
SARM users who seek our harm reduction services typically have implemented Ostarine-only cycles, dosed at 20 mg/day for 8 weeks. Users primarily cycle Ostarine to:
- Burn fat
- Retain muscle
- Gain strength
Men commonly adopt the above cycle protocol, whereas women typically administer 10 mg/day for 4–8 weeks.
Although we advise against it, some of our patients may cycle Ostarine for up to 12 weeks. Users typically extend the cycle only if cholesterol, liver, and testosterone values have not deteriorated excessively from the first 8 weeks of use.
Bodybuilders commonly cycle Ostarine alongside other SARMs. However, this approach is not recommended due to further elevations in blood pressure and liver enzymes.
Ostarine and GW501516 Cycle
| Week(s) | Ostarine | GW501516 (Cardarine) |
|---|---|---|
| 1–8 | 20 mg/day | 20 mg/day |
Some bodybuilders commonly stack Ostarine with GW501516 for more prominent fat loss. GW501516 does not belong to the SARM class; it activates peroxisome proliferator-activated receptor delta.
GW501516 has positive effects on:
- Insulin sensitivity
- Fatty acid oxidation
Preclinical studies indicate that GW501516 significantly reduces adipose tissue (5). Our patients also frequently experience notable weight loss during cycles of GW501516.
A randomized controlled trial has demonstrated that GW501516 has cardioprotective properties by increasing HDL cholesterol levels (6). Men and women under our care have experienced improvements in cardiovascular health while taking Cardarine, with a reduced frequency of breathlessness during exercise.
However, Thomas O’Connor, M.D., has reported hepatotoxic effects associated with GW501516, based on his analysis of laboratory data from over 2,000 SARM users. Dr. O’Connor compares the hepatotoxic effects of GW501516 to those observed with a daily dosage of 50 mg of Anavar. Consequently, concurrent use of GW501516 with Ostarine is likely to exacerbate adverse liver-related biomarkers.
Researchers have linked GW501516 to adverse effects that they have not adequately characterized since its initial appearance in scientific literature in 2001. Furthermore, its clinical use poses a potential carcinogenic risk (7). Long-term animal studies have demonstrated this risk by showing a correlation between administration and the development of various neoplasms.
The fitness community has criticized these studies for employing excessively high dosages. Nevertheless, research demonstrates that even the lowest doses of GW501516 possess carcinogenic potential. As a result, researchers remain skeptical regarding the safety of GW501516, which ultimately led researchers to discontinue its clinical trials in 2009.
How Can Researchers Administer Ostarine?
- Measure the dose with an eyedropper or syringe.
- Place the liquid in the subject’s mouth.
- Allow the liquid to sit under the tongue for 10–15 seconds before swallowing.
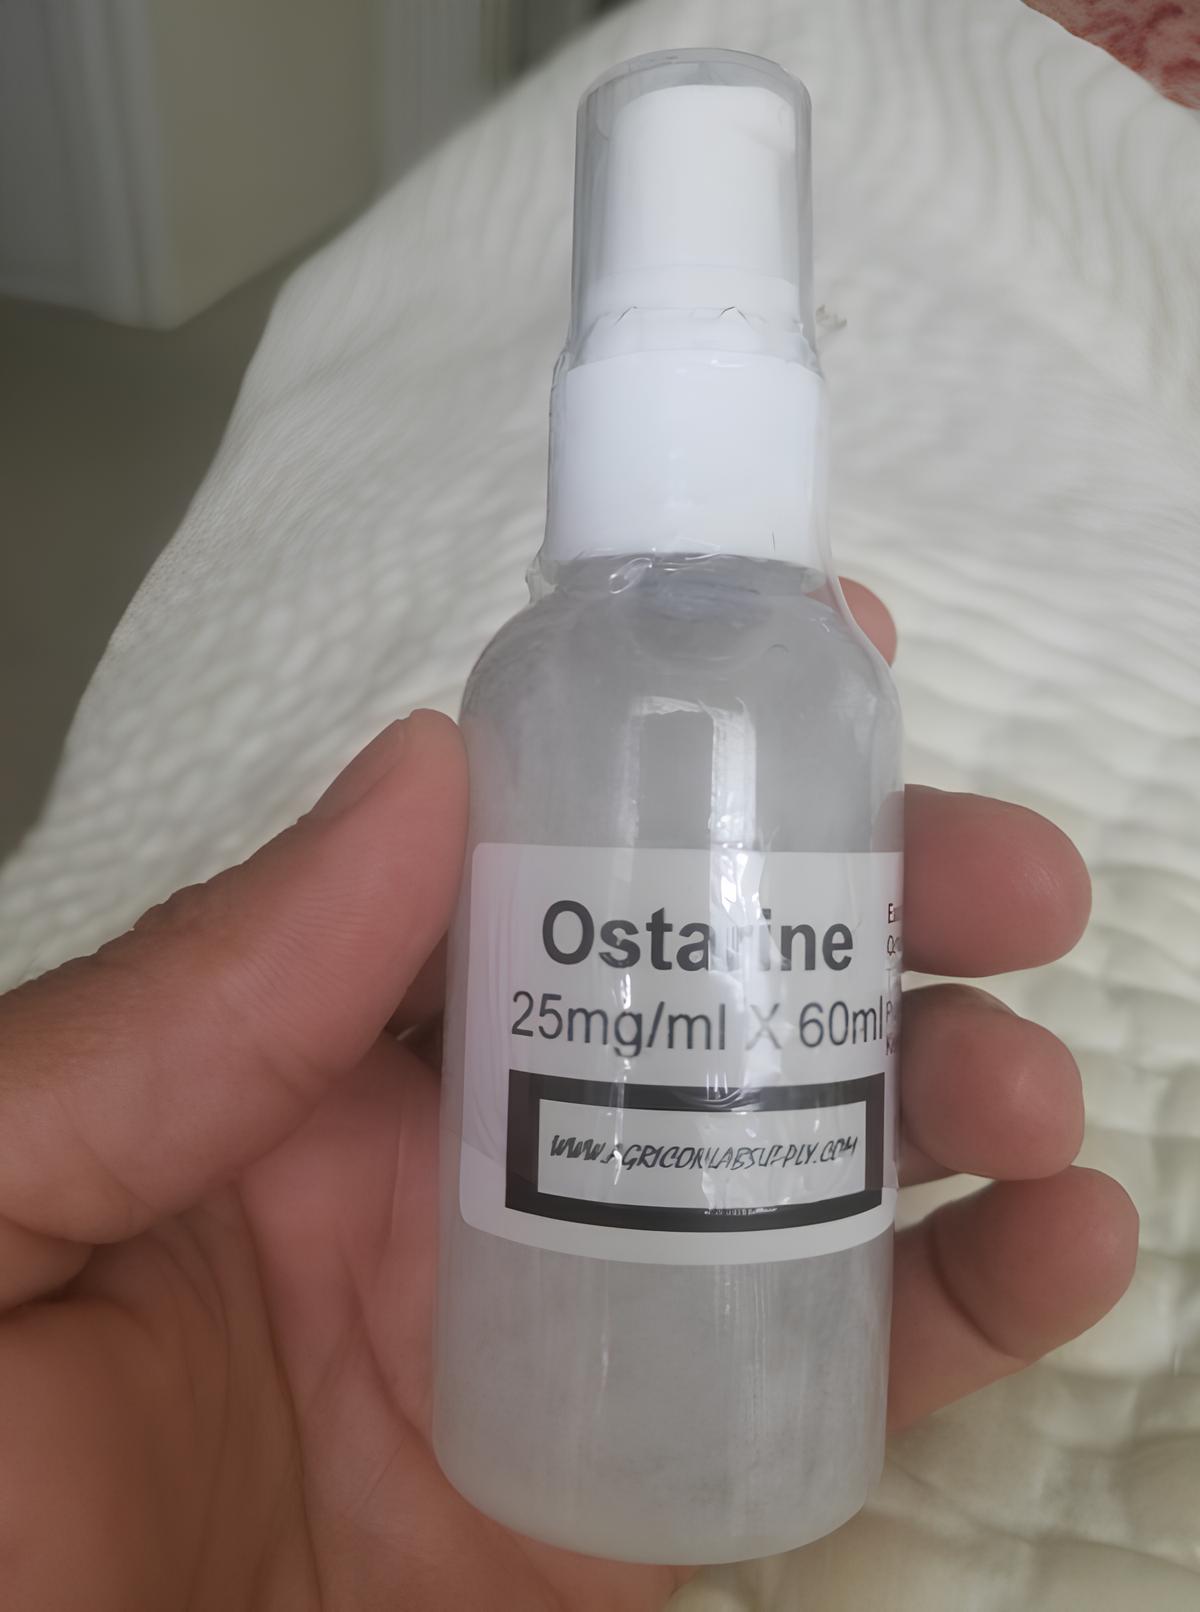
Researchers typically administer Ostarine orally, with manufacturers typically selling it in bottles containing a solution of 25 mg/mL.
We find that sublingual administration of the liquid allows it to penetrate the mucous membrane, creating a more direct and expeditious entry into the bloodstream (8). This placement also inhibits presystemic metabolism, increasing Ostarine’s biological availability.
Alternatively, manufacturers commonly formulate Ostarine in 10 mg capsules. Researchers conducting clinical trials may find these capsules particularly useful.
Top 5 Ostarine Sources: Tailored Recommendations for Researchers
- SwissChems
- Sports Technology Labs
- Biaxol
- UK SARMs
- Behemoth Labz
Researchers seeking a high-quality, laboratory-tested capsule may prefer SwissChems’ Ostarine. SwissChems also provides shipping outside of the US, benefiting foreign researchers.
Sports Technology Labs manufactures Ostarine in liquid and powder forms and offers one of the most affordable high-quality products for US researchers. It is over $30 cheaper than SwissChems’ Ostarine and may therefore be preferred by budget-conscious consumers.
Biaxol sells Ostarine in capsule form, which may suit researchers conducting clinical trials. Biaxol also offers international delivery, ensuring that scientists in even the most remote regions can access its products seamlessly.
MZ Biolabs, an independent laboratory, tests UK SARMs’ Ostarine, which demonstrates a high purity level that typically exceeds 98%. UK SARMs also offers next-day delivery, providing a fast and effective source for researchers in the United Kingdom.
Behemoth Labz is one of the few companies to formulate Ostarine in capsule, liquid, and injectable forms. This versatility makes it an attractive choice for researchers looking for flexible administration options.
Counterfeiters frequently imitate Ostarine and other SARMs. To mitigate the risk of scams or ineffective products, we advise consumers to purchase from reputable companies that provide third-party COAs for each product they sell. These reports confirm the presence of Ostarine and specify its purity levels.
Frequently Asked Questions
Can Ostarine Cause Bloating?
Several of our patients have experienced bloating from Ostarine. For some users, the bloating stopped after a couple of weeks of supplementation. However, for other users, bloating persisted until the cessation of the cycle.
Anti-estrogen medications can combat the following side effects of Ostarine and other SARMs:
- Water retention
- Bloating
- Low testosterone
- Decreased spermatogenesis
Several anti-estrogen products that bodybuilders use are:
- Arimidex (anastrozole)
- Femara (letrozole)
- Aromasin (exemestane)
Is 10 Milligrams of Ostarine Efficacious?
We have observed 10 mg/day to be a standard Ostarine dose among our female patients. This level is the lower end of a typical Ostarine dosage for males. Such a dosage can produce fewer side effects than larger dosages, in conjunction with decreased anabolism and lipolysis.
What is the Price of Ostarine?
The price of Ostarine varies depending on the source. We find that higher-quality products are typically priced higher due to increased manufacturing costs and superior purity levels. Below is a list of current Ostarine prices:
- Sports Technology Labs: $54.99
- SwissChems: $85.95
- Behemoth Labz: $79.95
Should Ostarine Be Taken on an Empty Stomach?
Our patients have taken Ostarine with and without food, and they reported no perceivable differences regarding body composition changes.
When is the Most Optimal Time to Take Ostarine?
For some users, taking Ostarine in the evening can cause insomnia. Thus, our patients typically administer Ostarine in the morning and repeat the dose every 24 hours.
What Duration is Required to Observe Results?
Our patients have reported experiencing results within the first two weeks of Ostarine use (1). Fluctuations in weight are not a reliable indicator of results because of simultaneous muscle gain and fat loss.
What is the Half-Life of Ostarine?
The half-life of Ostarine is 24 hours.
What is the Detection Time of Ostarine?
Ostarine’s detection time is estimated by multiplying its half-life of 24 by 5 to 7. Therefore, the detection time for Ostarine is approximately 120–168 hours.
Can Users Consume Ostarine Pre-Workout?
Ostarine is not intended for human consumption outside of clinical trials.
How Does Ostarine Compare to Other SARMs?
| SARM | Anabolic Strength | Side Effects |
|---|---|---|
| Ostarine | Mild to moderate | Mild |
| RAD-140 | Moderate | Moderate |
| LGD-4033 | Moderate | Moderate |
| S23 | Strong | Severe |
| Andarine (S-4) | Mild | Mild |
| YK-11 (Myostine) | Strong | Severe |
What Are the Contraindications for Ostarine?
Ostarine is not an FDA-approved medication; therefore, there are no officially established contraindications at this time. However, subjects with elevated liver enzymes or high cholesterol can be more susceptible to side effects from Ostarine, as it has been shown to:
- Cause hormone imbalances
- Elevate liver enzyme levels
- Increase cholesterol levels
Are There Any Viable Alternatives to Ostarine?
Companies have designed supplements to mimic Ostarine’s effects, such as OSTA 2866, which CrazyBulk manufactures. CrazyBulk’s formula contains only natural and FDA-approved ingredients. Consequently, OSTA 2866 users are unlikely to experience any side effects associated with Ostarine. However, according to our patients, such supplements are not as potent as Ostarine or other SARMs.
Has Ostarine Caused Diabetes in Clinical Research?
No clinical reports show that Ostarine causes diabetes. However, our tests indicate that Ostarine can decrease fasting blood glucose by 11%, based on patient data.
Therefore, individuals who administer the following medications in conjunction with Ostarine may experience complications from excessive lowering of blood glucose:
- Metformin (Glucophage)
- Glipizide (Glucotrol)
- Glyburide (Micronase)
- Pioglitazone (Actos)
- Exenatide (Byetta)
- Liraglutide (Victoza)
- Dulaglutide (Trulicity)
- Semaglutide (Ozempic)
- Insulin (Humulin)
Do Certain Athletes Supplement With Ostarine?
Various sporting federations have banned athletes from using Ostarine, as it can create an unfair advantage regarding:
- Muscular strength
- Power
- Endurance
However, such regulations have not stopped certain competitors from cycling Ostarine. Nikita Novikov was among the first athletes whose tests detected Ostarine. The Russian Anti-Doping Agency (RUSADA) consequently suspended the Russian cyclist for two years.
Below are several other high-profile athletes whose drug tests detected MK-2866:
- Ryan Garcia
- Amir Khan
- Sean O’Malley
- Tom Lawlor
- Lucian Bute
Ostarine Data and Information
| Topic | Details |
|---|---|
| Other names for Ostarine | Enobosarm, MK-2866, GTx-024, S22, and VERU-024 |
| IUPAC name | ((2S)-3-(4-cyanophenoxy)-N-[4-cyano-3-(trifluoromethyl)phenyl]-2-hydroxy-2-methylpropanamide) |
| CAS number | 841205-47-8 |
| Formula | C₁₉H₁₄F₃N₃O₃ |
| Molar mass | 389.334 g·mol⁻¹ |
Safety Guidelines
- There are numerous counterfeit Ostarine products; thus, researchers should exercise caution when purchasing online.
- We advise researchers to verify the legitimacy of the COAs by contacting the third-party laboratory.
- Ostarine is illegal for cosmetic use.
- The long-term effects of Ostarine are unknown.
- Check the bottle’s expiration date before administration.
- Clinicians should conduct blood tests to monitor organ health and hormone levels during Ostarine treatment.
- In clinical settings, do not exceed the dosage specified by the medical professional(s) leading the study.
- Store Ostarine products in a dry location, away from sunlight.
Anavar, an oral steroid, may pose fewer risks than Ostarine because researchers have studied its effects for several decades.
However, Anavar exhibits similar side effects to Ostarine, including:
- Cholesterol alterations
- Raised liver enzymes
- Testosterone suppression
In previous research, the side effects of Anavar at therapeutic doses have been unproblematic (9); hence, its former FDA-approved status in medicine.
Despite the FDA’s removal of Anavar as a treatment for muscle wasting, our patients find Anavar’s risk-to-reward ratio to be more favorable than Ostarine’s (10), due to it producing superior results in terms of:
- Fat loss
- Strength
- Muscle hypertrophy
US law still prohibits people from buying Anavar, and clinicians cannot prescribe it.
Summary: What Are the Pros and Cons of Ostarine?
Pros
- Decreases fat mass
- Increases lean muscle mass
- Enhances strength
Cons
- Potential toxicity
- Not as potent as other SARMs
Ostarine exhibits potent fat-burning properties attributed to its positive effects on insulin sensitivity and stimulation of the androgen receptor.
Users typically gain modest lean muscle with Ostarine, and many consider those gains inferior to those achieved with more potent SARMs, such as:
- LGD-4033
- RAD-140
- S23
- RAD-150
The fitness community often underestimates the severity of SARMs’ side effects. Even milder SARMs, such as Ostarine, can cause toxicity to the heart and liver. Testosterone suppression can also occur, negatively affecting the HPTA.
Olson et al. (2012) suggest that Clomid may accelerate HPTA recovery and shorten the period of low-testosterone symptoms (11).
Resources
- The wonder drug that’s plaguing sports
- Ostarine: the ‘invisible’ doping threat trapping innocent athletes
- Two cases underline the dangers of supplement contamination
- Veru announces the selection of a novel modified-release oral enobosarm formulation for chronic weight loss management following a pharmacokinetic clinical study
- Ryan Garcia tested positive for Ostarine before and after the Devin Haney fight
Relevant Research
- Absorption, distribution, metabolism, and excretion of the novel SARM GTx-024 [(S)-N-(4-cyano-3-(trifluoromethyl)phenyl)-3-(4-cyanophenoxy)-2-hydroxy-2-methylpropanamide] in rats
- Breakthrough in cachexia treatment through a novel SARM
- Ostarine-induced myogenic differentiation in C2C12, L6, and rat muscles
Co Authors :

Dr. Thomas O’Connor is the first American board-certified internist to focus his medical practice specifically on the health and recovery of individuals who use anabolic steroids and androgens.
He founded Testosteronology®, a dedicated subspecialty of internal medicine that addresses steroid-induced hypogonadism and associated cardiovascular and metabolic concerns.
Dr. O’Connor has over 20 years of experience treating men and women with a history of anabolic steroid, SARM, and PED use. He has been a board-certified MD since 2005 and provides guidance on harm reduction methodologies.
Dr. O’Connor is a clinical instructor at the University of Connecticut School of Medicine and has been featured in various media publications, including Generation Iron, Dr. Phil, National Geographic, The New York Times, Muscle and Fitness, and others.
Dr. O’Connor also co-authored the largest survey on anabolic steroid use, which involved 2,385 men and was published in the peer-reviewed American Journal of Men’s Health. He holds active medical licenses in Connecticut and Florida.
Additional research
- ACG Case Reports Journal: In a 2021 case study, a person developed jaundice after supplementing with Ostarine for 8 weeks, receiving a diagnosis of centrilobular cholestasis (12).
- Journal of Pharmaceutical and Biomedical Analysis: After cycling over 74 miles during a 10-week stack of Ostarine and Cardarine, a person developed an extreme case of rhabdomyolysis. Kintz, P. (2022) reports that they consumed 20 mg/day of each substance (13).
- Journal of Medical Cases: A user experienced itching and dark urine following 2 weeks of Ostarine use in a 2022 case report (14).
- JBJS Case Connector: Gould et al. (2021) documented a 36-year-old individual with an Achilles tendon rupture following a couple of 4-week cycles of Ostarine and Cardarine (15).
- The Lancet Oncology: Male and female cancer patients experienced significant muscle growth on Ostarine during a 16-week study (16).
- Asian Journal of Sports Medicine: A study found that Ostarine exhibited no adverse effects on LDL cholesterol after 8 weeks of supplementation (18).
- Journal of Bone and Mineral Metabolism: Moderate and high doses of Ostarine increased bone mineral density in female rats during an 8-week study (19).
- International Journal of Impotence Research: According to Efimenko et al. (2022), 22% of Ostarine users report testicular atrophy (20).
- The Lancet Oncology: Research indicates that fatigue, anemia, nausea, and diarrhea are side effects associated with Ostarine at doses of 1 mg and 3 mg per day (16).
References
- Dalton, J. T., Barnette, K. G., Bohl, C. E., Hancock, M. L., Rodriguez, D., Dodson, S. T., Morton, R. A., & Steiner, M. S. (2011). The selective androgen receptor modulator GTx-024 (enobosarm) improves lean body mass and physical function in healthy elderly men and postmenopausal women: results of a double-blind, placebo-controlled phase II trial. Journal of cachexia, sarcopenia and muscle, 2(3), 153–161. https://pubmed.ncbi.nlm.nih.gov/22031847/
- Ostarine increases lean body mass and improves physical performance in healthy elderly subjects: Implications for cancer cachexia patients. (2007). Journal of Clinical Oncology, 25(18_suppl), 9119-9119. https://ascopubs.org/doi/abs/10.1200/jco.2007.25.18_suppl.9119
- Flores, J. E., Chitturi, S., & Walker, S. (2020). Drug‐induced liver injury by selective androgenic receptor modulators. Hepatology Communications, 4(3), 450-452. https://journals.lww.com/hepcomm/fulltext/2020/03000/drug_induced_liver_injury_by_selective_androgenic.11.aspx
- Chong, S., Woolnough, C. A., Koyyalamudi, S. R., & Perera, N. J. (2024). Reversible Gynecomastia and Hypogonadism Due to Usage of Commercial Performance-Enhancing Supplement Use. JCEM case reports, 2(8), luae148. https://pmc.ncbi.nlm.nih.gov/articles/PMC11321837/
- Chen, W., Gao, R., Xie, X., Zheng, Z., Li, H., Li, S., Dong, F., & Wang, L. (2015). A metabolomic study of the PPARδ agonist GW501516 for enhancing running endurance in Kunming mice. Scientific Reports, 5, 9884. https://www.ncbi.nlm.nih.gov/labs/pmc/articles/PMC4421799/
- Olson, E. J., Pearce, G. L., Jones, N. P., & Sprecher, D. L. (2012). Lipid effects of peroxisome proliferator-activated receptor-δ agonist GW501516 in subjects with low high-density lipoprotein cholesterol: characteristics of metabolic syndrome. Arteriosclerosis, Thrombosis, and Vascular Biology, 32(9), 2289-2294. https://pubmed.ncbi.nlm.nih.gov/22814748/
- Mitchell, J. A., & Bishop-Bailey, D. (2019). PPARβ/δ: A potential target in pulmonary hypertension blighted by cancer risk. Pulmonary Circulation, 9(1), 2045894018812053. https://pmc.ncbi.nlm.nih.gov/articles/PMC6475847/
- Wang, Z., & Chow, M. S. (2014). Overview and appraisal of the current concept and technologies for improvement of sublingual drug delivery. Therapeutic Delivery, 5(7), 807–816. https://pubmed.ncbi.nlm.nih.gov/25287387
- Narayanan, R., Mohler, M. L., Bohl, C. E., Miller, D. D., & Dalton, J. T. (2008). Selective androgen receptor modulators in preclinical and clinical development. Nuclear Receptor Signaling, 6, e010. https://pmc.ncbi.nlm.nih.gov/articles/PMC2602589/
- Demling, R. H., & DeSanti, L. (1997). Oxandrolone, an anabolic steroid, significantly increases the rate of weight gain in the recovery phase after major burns. The Journal of trauma, 43(1), 47–51. https://pubmed.ncbi.nlm.nih.gov/9253907/
- Ribeiro, R. S., & Abucham, J. (2009). Recovery of persistent hypogonadism by clomiphene in males with prolactinomas under dopamine agonist treatment. European Journal of Endocrinology, 161(1), 163–169. https://pubmed.ncbi.nlm.nih.gov/19359408/
- Bedi, H., Hammond, C., Sanders, D., Yang, H. M., & Yoshida, E. M. (2021). Drug-induced liver injury from enobosarm (Ostarine), a selective androgen receptor modulator. ACG Case Reports Journal, 8(1), e00518. https://pubmed.ncbi.nlm.nih.gov/34368386/
- Kintz, P. (2022). The forensic response after an adverse analytical finding (doping) involving a selective androgen receptor modulator (SARM) in human athletes. Journal of Pharmaceutical and Biomedical Analysis, 207, 114433. https://pubmed.ncbi.nlm.nih.gov/34715583/
- Weinblatt, D., & Roy, S. (2022). Drug-induced liver injury secondary to enobosarm: A selective androgen receptor modulator. Journal of Medical Cases, 13(5), 244–248. https://pubmed.ncbi.nlm.nih.gov/35655632/
- Gould, H. P., Hawken, J. B., Duvall, G. T., & Hammond, J. W. (2021). Asynchronous bilateral Achilles tendon rupture with selective androgen receptor modulators: A case report. JBJS Case Connect, 11(2), 10. https://pubmed.ncbi.nlm.nih.gov/33835995/
- Dobs, A. S., Boccia, R. V., Croot, C. C., Gabrail, N. Y., Dalton, J. T., Hancock, M. L., Johnston, M. A., & Steiner, M. S. (2013). Effects of enobosarm on muscle wasting and physical function in patients with cancer: A double-blind, randomised controlled phase 2 trial. The Lancet Oncology, 14(4), 335–345. https://pubmed.ncbi.nlm.nih.gov/23499390/
- Vasilev, V., Boyadjiev, N., Hrischev, P., et al. (2024). Ostarine blunts the effect of endurance training on submaximal endurance in rats. Naunyn-Schmiedeberg's Archives of Pharmacology, 397, 6523–6532. https://link.springer.com/article/10.1007/s00210-024-03030-w
- Vasilev, V., Boaydjiev, N., Deneva, T., Arabadzhiyska, D., Komrakova, M., et al. (2023). Effects of Ostarine and endurance training on some functional, hematological, and biochemical parameters in male rats. Asian Journal of Sports Medicine, 15(1), e138116. https://brieflands.com/journals/asjsm/articles/138116
- Hoffmann, D. B., Komrakova, M., Pflug, S., von Oertzen, M., Saul, D., Weiser, L., Walde, T. A., Wassmann, M., Schilling, A. F., Lehmann, W., & Sehmisch, S. (2019). Evaluation of ostarine as a selective androgen receptor modulator in a rat model of postmenopausal osteoporosis. Journal of Bone and Mineral Metabolism, 37(2), 243–255. https://pubmed.ncbi.nlm.nih.gov/29785666/
- Efimenko, I. V., Valancy, D., Dubin, J. M., & Ramasamy, R. (2022). Adverse effects and potential benefits among selective androgen receptor modulators users: A cross-sectional survey. International Journal of Impotence Research, 34(8), 757–761. https://pubmed.ncbi.nlm.nih.gov/34471228/





I have been taking Ostarine for a little over a year now and recently when I had my annual checkup my doctor became concerned that my LDL had risen and my HDL had dropped. My HDL was 65 and now is 49. He wanted to know what the heck I have been doing for this to happen. I can only think it is because of the Ostarine.
I am 71 yrs old and I know that the Ostarine is helped me but I need to stop taking it to see if my cholesterol levels improve. How long will the negative effect take to reverse when I stop taking it? Any suggestions for me?
Hi, Kathy.
At 71 years of age, significant cholesterol alterations are likely from Ostarine. Women should aim for HDL levels of 60 mg/dL and above, with 40 mg/dL being considered low and high-risk. Thus, 49 mg/dL is below the optimal level but not drastically low. Lowering the Ostarine dosage is likely to reduce cardiotoxicity, in conjunction with increasing unsaturated fat intake, which can raise HDL levels. Cardioprotective foods include nuts, avocados, olive oil, and fatty fish. Discontinuing Ostarine supplementation can improve cholesterol levels promptly, with blood pressure typically normalizing after 5 days, based on its half-life of 24 hours.